If a couple has been trying to conceive for a year without success, it’s a good idea to consider whether there might be a medical reason for the delay.
So what are the conditions that can reduce their fertility?


If a couple has been trying to conceive for a year without success, it’s a good idea to consider whether there might be a medical reason for the delay.
So what are the conditions that can reduce their fertility?
The cause is male-related in 21% of the couples, female-related in 33%, and in 39% of the couples, both male and female factors are involved.
For 7 % couples, no explanation has been found.
They are very diverse.
In rare cases, men may experience ejaculation problems that are physical in nature (such as severe diabetes or prostate surgery), but these are more often associated with psychological factors.
The sperm in semen may be too few in number (oligospermia), lack sufficient motility (asthenospermia), or contain an excessive number of abnormal sperm (teratospermia).
The causes can be found either in the pituitary gland, in the testicles, or in the sperm ducts.
This may be due to a dysfunction of the pituitary gland or the testes caused by insufficient secretion.
The testicles may be involved, particularly if, for unknown reasons, they have remained inside the abdomen, as they do during fetal development.
Certain diseases, treatments, or situations can also affect sperm production: mumps, chemotherapy for cancer.
Finally, the presence of varicose veins in the testicles can disrupt spermatogenesis.
Sperm may have genetic abnormalities, making them unable to fertilize an egg or only able to do so to a limited extent.
Sperm production may even cease entirely; this is known as azoospermia, an extremely rare condition.
Sperm travel through ducts as they leave the testicles to gain motility and be transported outward.
These may either be partially absent—a condition present since birth—or «blocked» as a result of a local infection.
Many products can affect male fertility.
That's certainly true for tobacco, alcohol, and drugs.
These days, the issue of the environment is often discussed.
Testicular tissue is very fragile and sensitive to physical factors—such as excessive heat (working in an overheated environment, or wearing underwear and jeans that are too tight, which raise the temperature of the testicles)—and environmental chemicals, starting as early as the fetal stage.
Female causes include fallopian tube abnormalities (32 %), ovulation disorders (30 %), endometriosis (20 %), and recurrent miscarriages (2 to 5 %).
In nearly 10 % of cases, the test results are normal and no cause is found.
There is one very specific factor that contributes to a decline in female fertility: age.
Starting at age 30, female fertility begins to decline and the miscarriage rate increases.
While the average time it takes to conceive between the ages of 20 and 30 is six months, it gradually increases.
Fertility declines sharply starting at age 37.
The absence of ovulation or poor-quality ovulation can have various causes: it may be due to a disorder affecting the regulation of ovulation by the pituitary gland and the hypothalamus, a disorder affecting ovarian function, or, more rarely, a disorder affecting the adrenal glands.
When a fallopian tube becomes infected with a disease—particularly a sexually transmitted infection—it closes up.
If the condition is bilateral, fertilization becomes impossible because the sperm can no longer reach the egg, which is waiting at the end of the fallopian tube immediately after ovulation.
It is also a factor that increases the risk of an ectopic pregnancy.
Endometriosis is a very unique condition.
Its mechanism is still not well understood.
Menstrual blood contains cells from the uterine lining.
However, these cells sometimes migrate outside the uterus, toward the fallopian tubes, the ovaries, and the abdominal cavity.
There, they attach themselves and form microcysts.
Since these are hormone-dependent cells, they follow the ovarian cycle, causing slight bleeding inside the microcyst.
This can cause pain and damage around the uterus, such as adhesions.
It becomes difficult for the egg and a sperm to meet.
Uterine causes involve either the cervix or the uterine cavity itself.
After surgery on the cervix, fertility may decrease.
Most often, these are abnormalities in cervical secretions known as «mucus» or «cervical mucus.».
It is necessary for receiving sperm during sexual intercourse.
It plays a crucial role in sperm penetration, storage, and subsequent fertility.
Uterine malformations may be a contributing factor.
Recurrent miscarriages may be related to uterine abnormalities or immune-related causes.
Tobacco has a recognized and significant harmful effect.
For women who smoke ten cigarettes a day, it takes about twice as long to conceive.
The miscarriage rate is higher, and smoking has harmful effects on the embryo.
Obesity and being underweight are factors that contribute to reduced fertility.
Exposure to a number of chemicals has been suggested, but here, too, further investigation is needed.
In nearly 7 % of cases, medical examinations fail to identify any explanation.
This is what is known as functional infertility.
Everyone knows those couples who end up getting pregnant after adopting, after brushing off the doctors, or simply after painfully coming to terms with the fact that they won’t have children—and then turning their attention to other plans!
Ultrasound, hormone testing, semen analysis… several tests are recommended as part of an infertility evaluation.
These tests, which vary in invasiveness, are performed on both men and women.

It helps detect ovulation disorders.
In practical terms, this means taking your temperature every morning at the same time.
A normal curve shows fluctuations of a few tenths (at least 2): at the beginning of the cycle, the temperature is low; then it drops sharply on the day of ovulation and rises above 37 in the second half of the cycle after ovulation.
It then remains stable, but at a higher level than at the beginning of the cycle, until the onset of menstruation.
Learn more about the temperature curve.
This is one of the first things the doctor asks you to do.
A pelvic ultrasound can detect certain ovarian abnormalities (cysts, etc.) and uterine abnormalities (fibroids, polyps, malformations, endometriosis, etc.).
If a condition is suspected, further tests are ordered.
Infertility issues may be related to hormonal disorders.
It is therefore essential to measure the levels of certain hormones in the blood to confirm their presence and determine their concentration.
We thus measure levels of estradiol (which stimulates follicle growth under the influence of FSH), FSH (which enables a follicle to mature each month), LH (which triggers ovulation), progesterone (an indicator of normal ovarian function), prolactin (excess levels disrupt ovulation), and sometimes inhibin B and anti-Müllerian hormone (which provide additional information about ovarian reserve, reflecting the age of the ovaries).
It is important to have these tests done at the right time in the menstrual cycle.
This is an analysis of semen obtained through masturbation at the testing laboratory.
This allows us to observe sperm motility and count the sperm.
Semen normally contains between 20 and 400 million sperm cells. If there are fewer than that, the condition is called oligospermia.
The term "azoospermia" refers to the absence of sperm.
Finally, asthenospermia refers not to the number of gametes but to their low motility, which is nevertheless essential for reaching and then fertilizing the egg.
If the semen analysis shows «abnormalities,» it is recommended that you have another one done two to three months later.
This involves a vaginal swab, which must be processed in a laboratory within a few hours of sexual intercourse.
This allows us to examine the behavior of sperm in cervical mucus.
We can also analyze cervical mucus—its texture and quantity—which are essential factors in fertility.
However, this test is not a substitute for a semen analysis.
This is an X-ray exam that uses a contrast agent to determine whether the fallopian tubes are blocked.
This examination also allows for a good view of the uterus.
We usually take several photos.
The results are immediate.
In very rare cases of male infertility, there is a dysfunction of the hypothalamic-pituitary axis.
Patients are prescribed the equivalent of the pituitary hormones FSH and LH, which yields good results.
They are administered as intramuscular injections every two or three days for four to six months.
In addition, hormone therapy may be considered to restore testicular function.
In other forms of infertility, outcomes are often unpredictable, but hormone therapy may be initiated to improve sperm quality, possibly prior to assisted reproduction.
Prostate infections (prostatitis) and sexually transmitted diseases (STDs) must be treated with antibiotics, which will be prescribed for at least one month.
Corticosteroids may be beneficial in combating the antibodies produced by the body that attack its own sperm.
If the semen analysis is normal and shows no serious abnormalities, the doctor will focus on the patient’s lifestyle and recommend that he:
> Lead a regular lifestyle and stay physically fit
> Avoid heat in the testicular area: hot baths, underwear, or pants that are too tight. As a fun fact, heated underwear was once considered as a method of contraception.
In fact, spermatogenesis is optimal when the temperature of the testicles is slightly above 37°.
> Be cautious about sports such as horseback riding or cycling. By causing microtraumas, they could exacerbate the problem for men with low fertility.
> Avoid tobacco, coffee, alcohol, and overwork.
> Have sex often, without falling into a grueling routine that could «wear out» the sperm and the couple.
From childhood onward, some young boys undergo surgery when their testicles have remained abnormally in the abdominal cavity during fetal development instead of descending into the scrotum.
This condition requires surgery because it not only risks impairing these children’s future fertility but, more importantly, increases the risk of testicular cancer.
When there is dilation of the veins in the testicle (varicocele), surgical treatment involves ligating or occluding these veins.
Cet acte chirurgical rétablit la fécondité dans 30 à 50%des cas.
But keep in mind that 20% of men—whether fertile or not—are believed to have a varicocele, which, in most cases, does not cause any fertility problems.
Surgery may help restore the patency of the genital tract.
Permeability refers to the passage of gametes through the reproductive tract.
Even though it is achieved in 30 to 60% of cases, this does not mean a return to fertility.
In fact, many of these men also have an abnormality in sperm production.
Most andrologists—doctors who specialize in the male reproductive system—therefore now prefer to collect sperm directly from the epididymis for assisted reproductive technology.
The surgeon can perform the repermeabilization procedure at the same time as the sperm retrieval.
Infertility issues in women may require surgery as part of a diagnostic workup or to treat a specific cause.
Two techniques are most commonly used: hysteroscopy and laparoscopy.
Diagnostic hysteroscopy is used to check that the uterine cavity is normal and to perform biopsies.
It allows for the removal of a polyp that interferes with the implantation of an egg, the removal of a septum, or the severing of an adhesion (synechia).
It allows for a detailed examination of the entire female reproductive system.
During a diagnostic laparoscopy, the surgeon injects a blue dye into the uterus through the natural passages.
The passage of this substance through the ends of the fallopian tubes into the abdomen indicates that they are patent.
In patients with micro-polycystic ovary syndrome, this laparoscopic procedure involves making micro-punctures in the ovaries to induce ovulation.
Make 5 to 10 holes, each 5 to 10 mm deep.
In the event of an infection (such as appendicitis complicated by peritonitis), there is a risk that bacteria will spread throughout the abdomen.
The body defends itself by forming «firewalls» (adhesions) between the various organs.
Other conditions, such as endometriosis, can contribute to the formation of these adhesions.
These barriers can prevent the sperm from reaching the egg.
The goal is to address this issue by releasing these adhesions and using anti-adhesion agents in the abdomen.
This action clears the tip of a blocked proboscis.
The surgeon creates a new opening at the end of a blocked fallopian tube containing a clear fluid (hydrosalpinx).
Removal of diseased fallopian tubes is sometimes recommended to increase the chances of success with IVF.
This procedure, which restores patency to a fallopian tube following tubal sterilization, is possible only under certain conditions.
Success rates vary, and there is an increased risk of ectopic pregnancy.
In some cases, a fibroid can interfere with implantation or the development of a pregnancy.
Before recommending this procedure, it is important to confirm the link between the presence of the fibroid and infertility.
A myomectomy is the surgical removal of a fibroid.
Endometriosis can cause infertility.
Laparoscopy allows for the precise mapping of lesions, the collection of tissue samples, the destruction of lesions by burning them, the removal of diseased tissue, the reduction of pain, and the improvement of fertility.
Men also have breasts, although they are less developed than women's.
Breast cancer in men is rare. Less than 1 % of all breast cancers occur in men.
However, it is important for men to know that they can be affected by this cancer, especially so they do not ignore the symptoms.
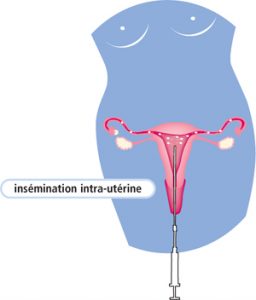
Artificial insemination is performed at an appropriate time during the cycle.
If the cycle is spontaneous, the time of ovulation is determined by the LH surge.
When the cycle is stimulated, ovulation is triggered by an intramuscular injection of the hormone HCG.
Insemination is performed between 24 and 48 hours after the LH surge or after induction with the hormone HCG.
It can be performed using fresh or frozen sperm from the spouse.
Intrauterine insemination is very common and enables one in three couples to avoid resorting to more invasive techniques.
The pregnancy rate achieved after one cycle ranges from 15 to 20%.
After 4 to 6 unsuccessful cycles, another assisted reproductive technology, such as in vitro fertilization, may be recommended.
This technique involves bringing sperm and oocytes together outside the female reproductive tract, in a culture medium that supports their survival in the laboratory.
The goal is to achieve fertilization and embryo development outside the body, hence the term “in vitro.”.
It is intended for women with blocked fallopian tubes, or in cases where other methods have failed—particularly after 4 to 6 artificial inseminations—or as a first-line treatment for women over the age of 38.
There are several steps involved in driving safely:
Success depends on the quality and number of oocytes retrieved.
To promote the development of ovarian follicles and obtain multiple oocytes, stimulation will begin with the daily administration of gonadotropins.
The dose is determined by the doctor based on several factors (age, weight, hormonal profile, antral follicle count on ultrasound, etc.).
This follicular maturation lasts an average of 12 days.
Since the number and rate of follicle development are unpredictable, medical monitoring is essential after a few days of injections.
It includes regular blood tests to measure hormone levels and ultrasounds.
This is the crucial moment in the treatment.
Once the follicles are mature (greater than 17 mm), treatment will be stopped .
An injection of hCG (Pregnyl®) or LH (Ovitrelle®) will artificially trigger the final response necessary for ovulation.
This injection must be given at a specific time, always in the evening, so that the eggs can be retrieved just before they leave the follicles—that is, the morning two days after the injection.
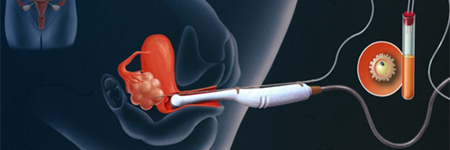
Egg retrieval will be performed 34 to 36 hours after the Pregnyl® (or Ovitrelle®) injection.
The egg has now reached full maturity and is located in the follicular fluid, from which it can be easily aspirated.
The procedure is performed using a needle inserted transvaginally, under ultrasound guidance and under general, sedation, or local anesthesia, in an operating room.
The collected follicular fluid is immediately sent to the biologists at the IVF laboratory to isolate the egg it contains.
The number of eggs retrieved varies widely. On average, about ten are retrieved.
At the same time, on the day of the egg retrieval, the partner must go to the laboratory to provide a semen sample. This sample is collected after a period of abstinence of approximately three days. It is possible to arrange for the semen to be frozen.
In some cases, a testicular biopsy or sperm aspiration from the ejaculatory ducts will be necessary. This procedure will be performed either before (frozen sperm) or on the same day (fresh sperm) as the egg retrieval, under general or local anesthesia.
Fertilization will be performed using conventional IVF or intracytoplasmic sperm injection (ICSI):
Fully matured eggs and »viable» sperm are combined in a biological culture medium conducive to their survival, and then stored in an incubator at 37°.
A sperm microinjection is performed:
This technique is called ICSI (Intracytoplasmic Sperm Injection).
This involves the introduction of a single sperm into the cytoplasm of the egg, under microscopic guidance using a high-precision device (a micromanipulator).
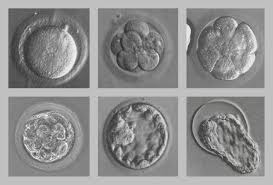
24 hours after fertilization, when the egg cell takes on the appearance of a cell containing two nuclei—one from the mother and one from the father—this indicates that fertilization has occurred.
This stage is called 2 PN, which stands for «two pronuclei.».
The fertilized eggs are returned to the incubator and examined under a microscope.
48 hours later, if the fertilized eggs have undergone their first cell division, they develop into embryos.
To promote their implantation in the uterine lining, it is possible to extend the in vitro development of the embryos.
They are then placed in an environment that provides them with the nutrients essential for their development.
Embryos can be transferred between the 5th and 7th day of culture or frozen for later transfer.
This is the moment when the embryo leaves the test tube and enters the mother's womb.
It’s a precious moment, as if we were making a promise.
It usually takes place two or three days after the egg retrieval.
The egg or eggs are placed in a very thin catheter that is inserted into the uterine cavity.
This procedure is quick and painless, and is sometimes followed by hormone therapy.
The woman can certainly resume her normal activities within a few days.
That's what everyone is hoping for.
This period is filled with a mixture of hope and anxiety.
After having been in constant contact with the medical staff, the couple now finds itself alone, left to wait.
A hCG hormone test, performed starting on the 12th day after the embryo transfer, indicates whether or not a pregnancy has occurred.
If the result is positive, a follow-up test is performed to confirm the pregnancy.

Dr Nadia Oukacha puts her expertise in gynecology, obstetrics and fertility at the service of every woman, combining listening, prevention and cutting-edge technology.
Each consultation begins with an in-depth discussion to understand your needs and establish a climate of trust.
A complete check-up, nutritional advice and psychological follow-up are adapted to your age and life situation.
Regular smear tests, screening and check-ups aim to anticipate risks and preserve your health over the long term.
Here you'll find answers to the most frequently asked questions about consultations, specialties, booking appointments and how the practice works.
You can book your consultation directly online via our website or by calling the practice on +212 606 12 12 13. A contact form is also available on the site.
Dr Oukacha specializes in :
Gynecology (consultations, pap smears, colposcopy, ultrasounds)
Obstetrics (pregnancy monitoring, ultrasound, amniocentesis)
Intimate and breast surgery
Fertility and medically assisted reproduction (MAP)
The practice is equipped for :
Gynecological and obstetrical ultrasounds
Cervico-vaginal smear
Colposcopy
Fertility assessment
Monday through Friday: 9:00 a.m. – 5:00 p.m.
Saturday: 9:00 am - 1:00 pm
Sundays and public holidays: closed
The office is located in Casablanca, at 125 BD Brahim Roudani, 1st floor, Appt 11. An interactive map is available on the Contact page.
Access specialized gynecology, obstetrics and fertility care with confidence and simplicity.